This site is not the association. US crisis calls: pwsausa.org · 941-312-0400. We do not answer that phone.
SURGERY AND ANAESTHESIA
Before surgery or anaesthesia in PWS: delayed stomach emptying, stress-dose steroids, and night-one airway monitoring.
Most families meet the anaesthesia team early: first for adenotonsillectomy after a pre-growth-hormone sleep study, for orchidopexy, for dental work, or later for scoliosis rods. General hospital checklists miss four syndrome-specific traps: a stomach that is not empty after an 8-hour fast, an outdated rule about routine stress-dose steroids, extreme sensitivity to post-op opioids, and a high pain threshold that hides surgical complications until late.
1 · FASTING IS NOT EMPTY
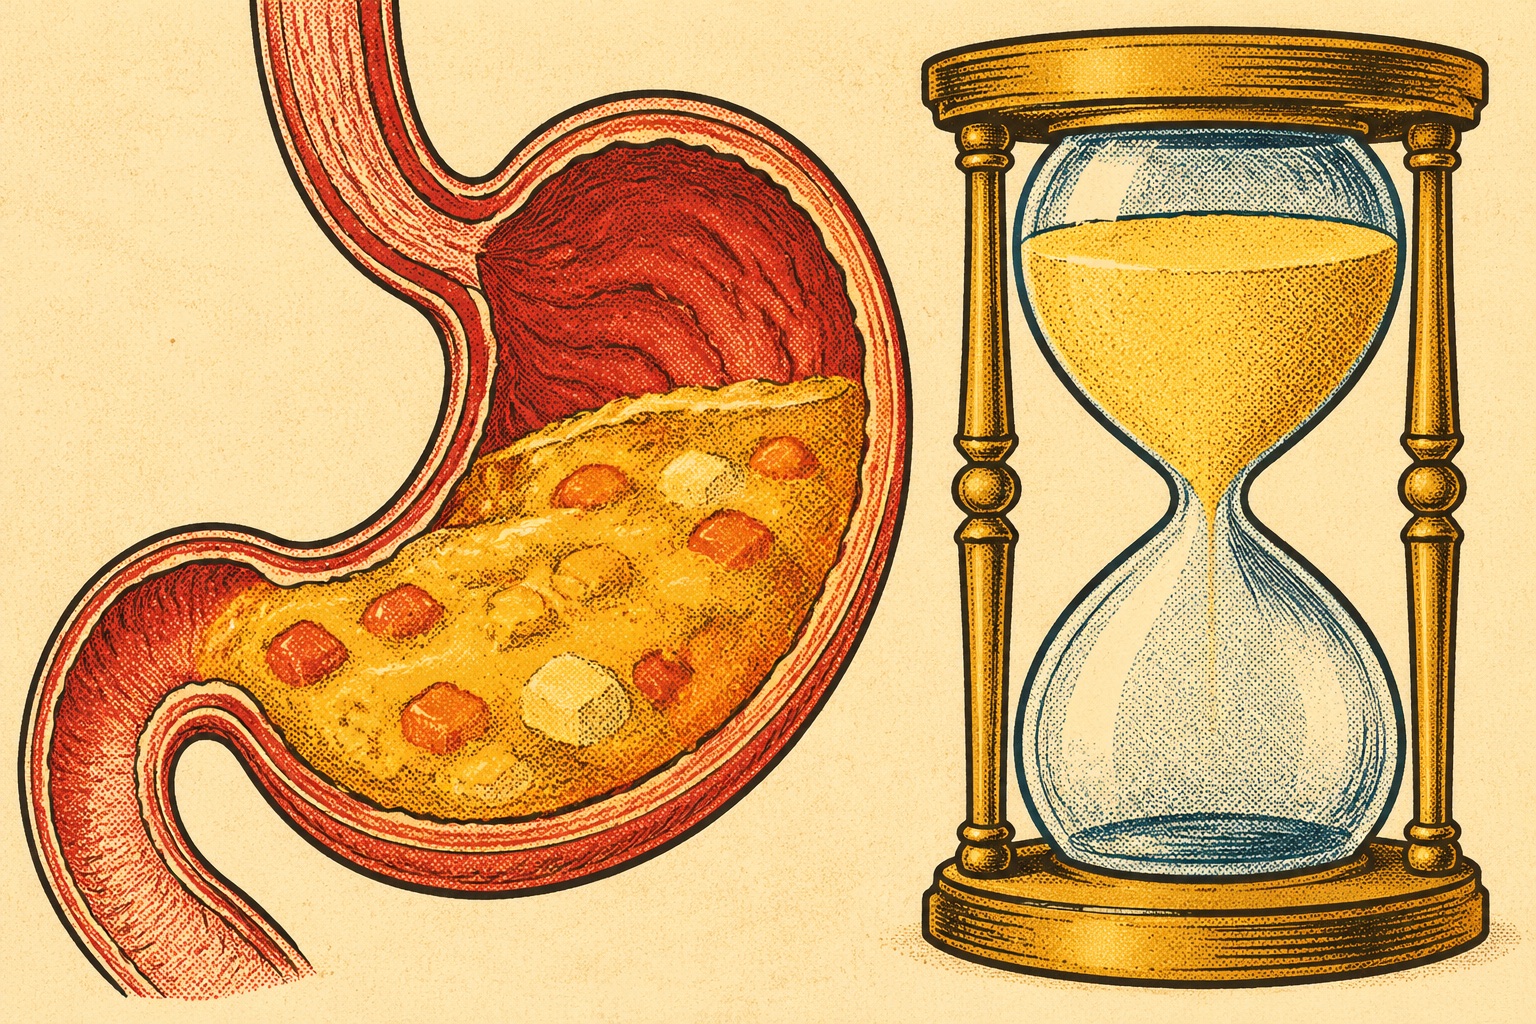
Gastric emptying is slow in PWS. Solid food can sit in the stomach past a routine 8-hour NPO window, and older children may sneak food before admission. Ask the anaesthetist about prolonged solid fasting, bedside gastric ultrasound, or full-stomach airway precautions.
2 · THE 1.2% CORTISOL DATA
Older pamphlets warned that up to 60 percent had central adrenal insufficiency. A 2020 international study tested 82 adults with metyrapone or insulin tolerance and found 1.2 percent (1 of 82); 200 surgeries without hydrocortisone had zero adrenal crises.
3 · OPIOIDS AND NIGHT ONE
Low muscle tone, central and obstructive sleep apnea, and blunted carbon-dioxide drive mean standard post-op opioid doses can trigger silent hypoventilation. The 2025 anaesthesia series uses nerve blocks, multimodal non-opioid pain control, and reverse Trendelenburg recovery.
4 · SCOLIOSIS AND GH
Scoliosis reaches 70 to 80 percent by skeletal maturity, with peaks in infancy and puberty. Growth hormone does not need to stop for scoliosis. When spine fusion is needed, a 2024 series reported a 75 percent complication rate: guard against skin picking and hardware infection.
WHAT CHANGED ON STRESS-DOSE STEROIDS
Why endocrinologists stopped giving automatic hydrocortisone to every PWS patient
In 2008, a small metyrapone study suggested that 60 percent of children with PWS had central adrenal insufficiency (CAI), and for a decade many centres gave stress-dose hydrocortisone during every fever and operation. Repeated steroid courses carry real cost in PWS: rapid weight gain, higher blood glucose, bone loss, and blood pressure rise.
Two larger datasets changed the picture. In 2020, Rosenberg and colleagues (Journal of Clinical Endocrinology and Metabolism) tested 82 adults across Europe using metyrapone or insulin tolerance tests and reviewed 645 medical records. True CAI appeared in 1 of 82 patients (1.2 percent). Among 200 surgical procedures performed without perioperative hydrocortisone, zero patients showed hypocortisolism. In 2022, a study of 128 growth-hormone-treated children with PWS (Journal of Pediatric Endocrinology and Metabolism) found a mean morning plasma cortisol of 9.7 plus or minus 3.7 ug/dL and normal morning ACTH (22.1 plus or minus 8.0 pg/mL), recommending morning cortisol and ACTH screening before considering dynamic testing or routine steroid cover.
Perioperative question
What older habits assume
What 2020 to 2026 evidence supports
Pre-op fasting (NPO)
Standard 6 to 8 hour solid fast guarantees an empty stomach.
Delayed gastric emptying and unrecorded food access can leave food or air in the stomach. Supervise the fast, consider longer clear-fluid windows or gastric ultrasound, and plan airway protection. See emergency.
Stress-dose hydrocortisone
Give automatic stress steroids to every child or adult with PWS for surgery.
True CAI was 1.2 percent in 82 tested adults (0 crises in 200 steroid-free surgeries) and morning cortisol was normal in 128 GH-treated children. Check morning cortisol and ACTH with the endocrine clinic before elective surgery.
Tonsillectomy before growth hormone
Moderate or severe sleep apnea on pre-GH polysomnography means GH is off the table.
2024 UK guidance and the 2022 sleep review state that obstructive apnea is treated (often adenotonsillectomy), the sleep study is repeated, and GH then starts. Watch overnight breathing after ENT surgery. See growth hormone.
Post-op pain and sedation
Dose morphine or fentanyl by body weight and wait for the patient to ask for help.
High pain threshold masks distress while obesity and hypotonia amplify opioid respiratory depression. Use regional nerve blocks and paracetamol or NSAIDs first, and keep continuous pulse oximetry and capnography on night one.
Scoliosis bracing and spine surgery
Stop growth hormone if the curve worsens; treat the spine like adolescent idiopathic scoliosis.
Cumulative scoliosis prevalence is 70 to 80 percent (bimodal: infancy and puberty). Keep GH to support muscle tone. In a 2024 spine series (15 patients, curves 14 to 102 degrees), 9 of 11 braced curves progressed and 3 of 4 surgical cases had complications (hardware infection, rod failure, neurological injury). Protect incisions from skin picking.
Common questions
Does every person with PWS need stress-dose hydrocortisone during surgery?
Not automatically. An international 2020 study tested 82 adults with PWS using metyrapone or insulin tolerance tests and found central adrenal insufficiency in only 1.2 percent (1 of 82); in 200 surgeries performed without perioperative hydrocortisone, zero patients developed hypocortisolism. A 2022 study of 128 GH-treated children found mean morning cortisol of 9.7 ug/dL, within the normal range. Check morning cortisol and ACTH with endocrinology before surgery rather than assuming universal deficiency.
Why is a standard 8-hour fast sometimes not enough before anaesthesia in PWS?
Gastric motility is slower in Prader-Willi syndrome, and some children or adults have ruminated or accessed food without caregivers knowing. Solid food can remain in the stomach past standard fasting windows, raising aspiration risk during induction. Pre-op teams often use longer solid-food fasting, gastric ultrasound, or rapid-sequence airway precautions.
Does growth hormone have to stop before tonsillectomy or scoliosis surgery?
No routine stop rule exists in the 2024 UK guidance or the 2026 endocrine-scoliosis framework. If moderate or severe obstructive sleep apnea is found before starting growth hormone, ENT treats the airway first. Once on growth hormone, keeping therapy maintains muscle tone and lean mass around spine care.